
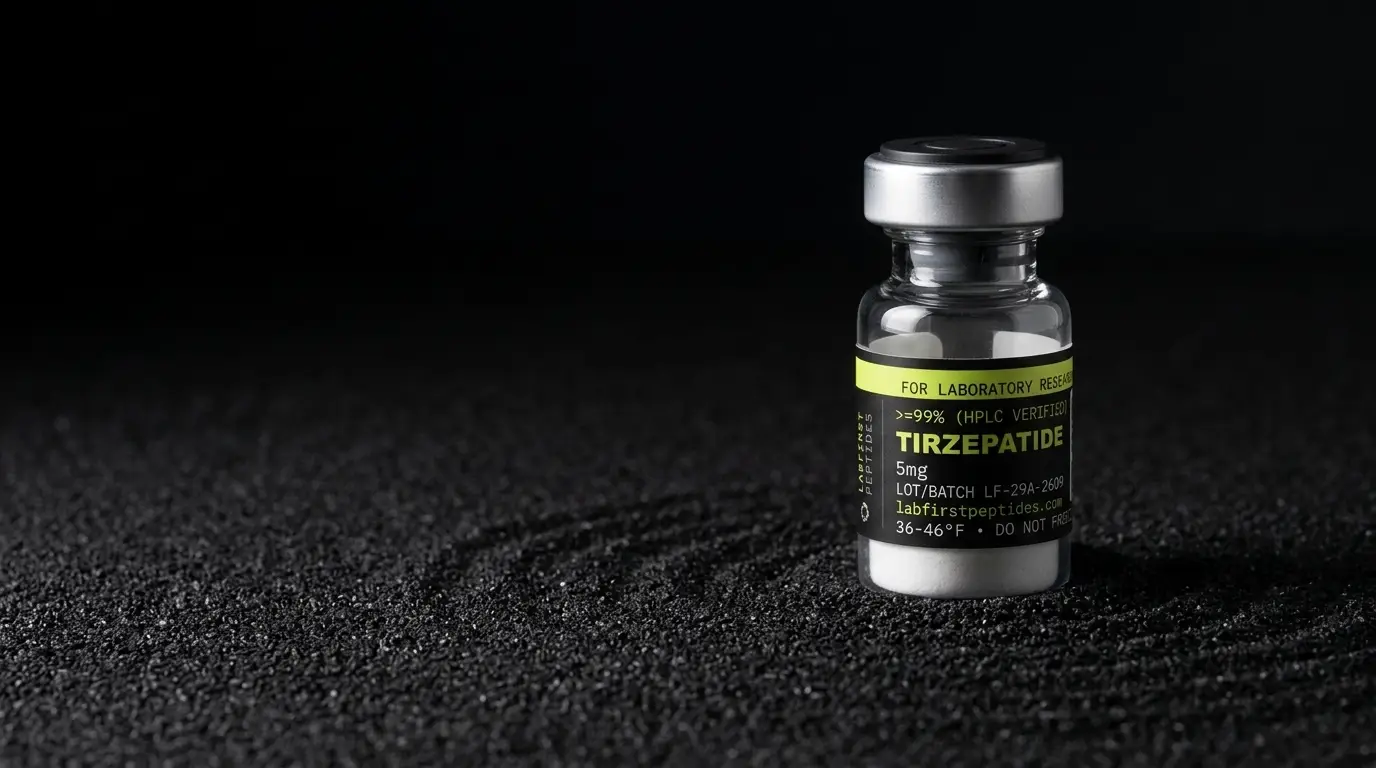
Compounded tirzepatide is a version of tirzepatide mixed by a pharmacy or outsourcing facility instead of made under an approved drug application. FDA says compounded drugs are not FDA approved. FDA declared the tirzepatide shortage resolved on December 19, 2024, which ended the shortage-based room compounders had relied on.
- FDA states that compounded drugs, including compounded tirzepatide, are not FDA approved and are not reviewed for safety, effectiveness or quality before marketing.
- FDA declared the tirzepatide shortage resolved on December 19, 2024.
- FDA's enforcement discretion for compounded tirzepatide ended February 18, 2025 for 503A pharmacies and March 19, 2025 for 503B outsourcing facilities.
- Section 503B outsourcing facilities must meet current good manufacturing practice and face risk-based FDA inspection, while 503A pharmacies are exempt from CGMP.
- PubChem lists tirzepatide (CID 166567236) as C225H348N48O68 with an average molecular weight of 4,813.
What this guide covers
A pharmacist in a back room weighs out powders and mixes a cream for one patient who can't use the store-bought version. That's compounding in its oldest form, and it's legal. The trouble starts when the same idea gets stretched to cover a new, high-demand drug.
This page explains what compounded tirzepatide is in regulatory terms, using FDA's own pages and the dates FDA gives. It covers the 503A and 503B routes, the shortage that opened a temporary window and then closed it, and why a vial of research-grade tirzepatide powder sits in a different category from any medicine. It gives no advice on getting, using or judging the safety of any medicine. Questions like that belong with a licensed clinician.
- Nov 27, 2013: DQSA sets 503A and 503B
- Shortage listing opens room for copies
- Dec 19, 2024: shortage resolved
- Feb 18, 2025: 503A discretion ends
- Mar 19, 2025: 503B discretion ends
What is compounded tirzepatide?
Compounded tirzepatide is tirzepatide prepared by a compounder rather than produced under an approved drug application. FDA defines compounding as a practice in which a licensed pharmacist, a licensed physician or, for an outsourcing facility, a person supervised by a licensed pharmacist "combines, mixes or alters ingredients of a drug to create a medication tailored to the needs of an individual patient."
The key regulatory point is approval. FDA states that compounded drugs are not FDA approved, "which means the agency does not review their safety, effectiveness or quality before they are marketed." An approved tirzepatide product went through that review. A compounded one did not, however carefully it was made.
The molecule itself is a synthetic peptide. PubChem lists tirzepatide (CID 166567236) with the formula C225H348N48O68 and an average molecular weight of 4,813. Our guide on whether tirzepatide is a peptide covers its structure in more depth.
What is the difference between 503A and 503B?
The two numbers are sections of the Federal Food, Drug, and Cosmetic Act, and they describe two kinds of compounder. Congress reshaped the system in the Drug Quality and Security Act, enacted November 27, 2013. FDA says Congress passed that law in response to the 2012 fungal meningitis outbreak.
| Point | 503A | 503B |
|---|---|---|
| Who | State-licensed pharmacies and physicians | Outsourcing facilities, a voluntary category created in 2013 |
| Orders | Prescriptions for individual patients | Patient-specific prescriptions or office stock for non-identified patients |
| Manufacturing standard | Exempt from CGMP | Must meet current good manufacturing practice |
| FDA inspection | Not on FDA's risk-based schedule | FDA inspects on a risk-based schedule |
Neither route produces an FDA-approved drug. Both sit inside limits, and one of the most important limits concerns copies of drugs that are already on the market.
Why could compounders make tirzepatide during the shortage?
The law generally keeps compounders from making copies of commercially available drugs. A drug on FDA's shortage list is treated differently, which gave compounders room to produce tirzepatide while supply was short.
FDA describes a compounded product as a copy when it has "the same active pharmaceutical ingredient(s) (API) as the commercially available drug product in the same, similar or an easily substitutable strength" and the same route of administration. The exception is when a prescriber documents that the compounded version carries "a change that produces a significant difference" for the patient.
So the shortage listing mattered a great deal. While tirzepatide was in shortage, the copy limit did not bite in the usual way. Once FDA said the shortage was over, compounders lost that footing.
When did FDA say the tirzepatide shortage ended?
FDA declared the tirzepatide shortage resolved on December 19, 2024. It then gave compounders a short wind-down period, in the form of enforcement discretion with fixed end dates.
| Event | Date FDA gives |
|---|---|
| Shortage declared resolved | December 19, 2024 |
| Enforcement discretion ends for 503A pharmacies | February 18, 2025 |
| Enforcement discretion ends for 503B outsourcing facilities | March 19, 2025 |
Those dates come from the FDA page on compounder policies as GLP-1 supply stabilized, which we read on October 11, 2026. The page showed a date of April 1, 2026. FDA's drug shortage database did not load when we checked, so this guide reports shortage status as of FDA's policy page rather than a fresh database lookup.
What does FDA say about compounded tirzepatide now?
FDA keeps a page on its concerns with unapproved GLP-1 drugs, updated October 1, 2026. It repeats that compounded drugs are not FDA approved and says they "should only be used in patients whose medical needs cannot be met by an FDA-approved drug." That sentence is FDA's policy position. We quote it as such and offer no view on any person's situation.
Two other points on that page are regulatory facts. FDA notes that some compounders have used salt forms of these molecules, and says it "does not have information on whether these salts have the same chemical and pharmacologic properties as the active ingredient in the approved drug." FDA also reports more than 730 adverse event reports involving compounded tirzepatide as of May 31, 2026. Those reports come from the public and from professionals. A report on its own does not show that a product caused an event.
Why the approval question matters for a lab reader
A lab worker reading about tirzepatide meets three different things under one name. There is the approved medicine, which passed FDA review. There is the compounded drug, made by a pharmacy or outsourcing facility and never reviewed by FDA before sale. And there is research material, which is a chemical for the bench.
Mixing those up causes real confusion. A forum post about a compounded product tells you nothing about a research lot, and a research certificate says nothing about any medicine. Keeping the three apart is the whole reason this page exists. When a source blurs them, treat its other claims with care too.
How does research-grade tirzepatide differ from a medicine?
Research-grade tirzepatide is lyophilized peptide powder sold for laboratory and in-vitro work. It is neither a compounded drug nor an approved one. It carries no labeling for any use in people, it is not made for a patient, and nothing about it should be read as a substitute for a medicine. Our page on what research use only means covers that label in full.
What a research buyer can check is the material itself: identity, purity by HPLC and the paperwork behind a specific lot. The tirzepatide identity guide explains how mass spectrometry matches a sample to the expected mass, and the tirzepatide certificate guide walks through each line of a certificate. Certificates for each lot are posted at /coa/.
FOR LABORATORY AND IN-VITRO RESEARCH USE ONLY. NOT FOR HUMAN OR ANIMAL CONSUMPTION.
How to check what FDA currently says: step by step
- Open FDA's page on its concerns with unapproved GLP-1 drugs and read the last-updated date near the bottom.
- Open FDA's compounder policy page for GLP-1 supply and note the shortage resolution date and the 503A and 503B end dates.
- Search FDA's drug shortage database for tirzepatide and read its current status line.
- If a status has changed since the dates on this page, trust FDA's newer page over this guide.
- For any question about a person's care, ask a licensed clinician. A supplier's guide is the wrong place for that answer.
What to check in any claim about compounded tirzepatide
- Does it say the product is FDA approved? FDA says compounded drugs are not.
- Does it describe a shortage as current? FDA declared the tirzepatide shortage resolved on December 19, 2024.
- Does it mention a salt form? FDA says it lacks information on whether those salts match the approved active ingredient.
- Does it give a date for its regulatory claims? An undated status line can't be checked.
- Does it cite FDA directly? A secondary summary can lag FDA's own page by months.
Bottom line
Compounding is a legal practice with defined lanes, and tirzepatide passed through those lanes in volume only while FDA listed it in shortage. FDA ended that shortage on December 19, 2024, set 503A and 503B wind-down dates in early 2025, and still says compounded drugs get no FDA review before sale. Research-grade tirzepatide powder belongs to the laboratory and carries no claim for anyone's health.
What is Tirzepatide studied for?
Published research on Tirzepatide investigates the areas below, which is a different question from what Tirzepatide will do for anyone, a claim about a living system that nothing on this site is sold for.
What it is. A peptide that works on the GIP and GLP-1 receptors at the same time.
What the research looks at. There is a large published clinical record: how it behaves at the receptors, how the body handles it, and the measurements its sponsor registered its trials to take. Approved medicines containing it exist under their own brand names.
How it is thought to work. It switches on both the GIP receptor and the GLP-1 receptor. Working on two rather than one is the design feature that separates it from the GLP-1-only drugs.
What is not established. What is sold here is a research chemical, not a drug product. Listing it is not an approval, and not a claim that it is equivalent to, as safe as, or a fit substitute for any approved medicine.
The full record, including the certificate for the lot in stock, is on the Tirzepatide product page.
Common questions
What is compounded tirzepatide?
Is compounded tirzepatide FDA approved?
Is tirzepatide still on the FDA shortage list?
How is a tirzepatide compound different from research-grade tirzepatide?
Why does FDA mention salt forms of compounded tirzepatide?
More science guides
Sources
- FDA: Human Drug Compounding. FDA's definition of compounding and its statement that compounded drugs are not FDA approved (content current as of June 15, 2026).
- FDA: Human Drug Compounding Laws. Sections 503A and 503B of the FD&C Act, outsourcing facilities, CGMP and the Drug Quality and Security Act of 2013.
- FDA: FDA clarifies policies for compounders as national GLP-1 supply begins to stabilize. Shortage resolution dates and the end of enforcement discretion for 503A and 503B compounders, plus FDA's description of a copy.
- FDA: FDA's concerns with unapproved GLP-1 drugs used for weight loss. FDA statements on compounded versions, salt forms and adverse event reports (page updated October 1, 2026).
- PubChem PUG REST: CID 166567236 (tirzepatide). Molecular formula and average molecular weight, read October 11, 2026.
